TriWest and VA Community Care Network Billing Delays and Claim Recovery
A claim-by-claim guide to recovering stalled VA and TRICARE West revenue.
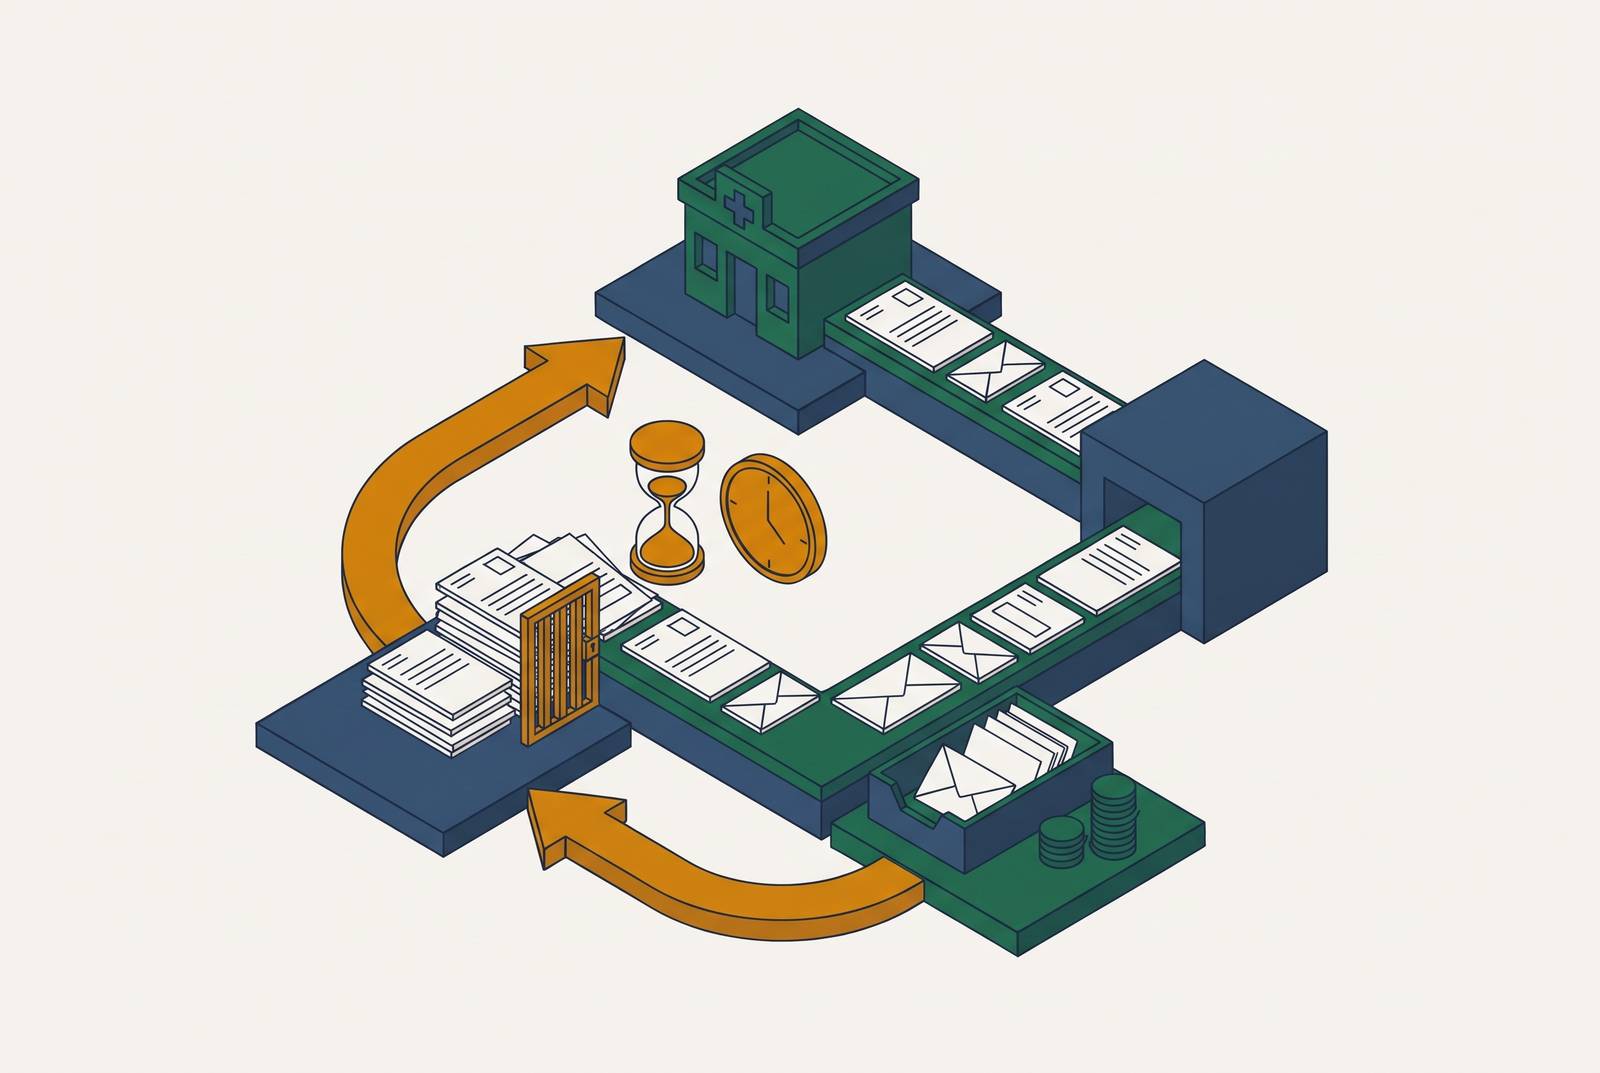
TriWest’s transition failures and the January 2026 claims hold have created recoverable revenue problems for practices billing VA Community Care and TRICARE West. To recover it, practices need to find where each claim stalled, sort administrative errors from valid denials, and act before the filing or dispute deadline for that claim. A general backlog campaign is not enough.
What practices billing VA Community Care and TRICARE West are actually dealing with right now
The Evans case shows how a congressional caseworker inquiry can produce faster administrative action than communication with TriWest alone. David Kraklow’s case shows the financial exposure when processing fails. The retired Marine Corps major in Temecula, California, accumulated nearly $700,000 in unpaid bills, including for surgery TriWest itself had authorized. His coverage was also incorrectly flagged for other insurance. Authorization did not prevent the payment breakdown.
TriWest and Humana Military both experienced problems loading provider files into their databases and claims systems in early 2025, producing a backlog of more than a million claims. The Defense Health Agency stated that both contractors met processing timeliness requirements from July 2025 onward. Yet patient and provider complaints documented through at least April 2026 contradict the implication that the problem was resolved. Rep. Marilyn Strickland described improvement as “too slow” in March 2026.
The January 2026 rate validation hold was a separate disruption. It should not be folded into the provider-file backlog, because the underlying cause and supporting recovery documentation differ. A claim delayed by provider data failures requires a different account of the interruption than one caught in rate validation.
Why the same failure keeps recurring: how the CCN billing structure creates systematic delay points
The VA Community Care Network is not a standard insurance arrangement. Optum administers Regions 1, 2, and 3, while TriWest administers Regions 4 and 5, with different systems, fee schedules, and administrative processes. Sending a claim to the wrong third-party administrator holds up the start of adjudication. Confusing a VA Community Care patient with a standard TRICARE beneficiary can send the claim through the wrong system entirely.
Under the CCN sequencing requirements, other primary coverage must be billed first, with the primary explanation of benefits attached to the CCN claim. Every CCN claim also requires the VA authorization number from the referral. Neither requirement is an optional administrative detail. Missing either can lead to a denial while time keeps running out in the relatively short timely filing window.
Payment introduces another layer of uncertainty because reimbursement follows a hierarchy, beginning with the Medicare fee schedule, then the VA fee schedule, and then a percentage of billed charges when neither applies. These weaknesses, including uncertainty about the applicable rate at submission, leave practices open to disputes even after they have been paid.
The six denial patterns that account for most stalled CCN and TRICARE West revenue
Practices first need to check whether an other health insurance denial stems from real coverage or an error in the payer’s data. TriWest’s database failures generated erroneous OHI flags for beneficiaries. Those claims need the administrative error fixed, with no need for proof that another insurer paid. By contrast, when a veteran has primary Medicare coverage and the practice failed to bill it first, the COB denial reflects a genuine sequencing failure. The remittance can look the same in both cases.
A missing or invalid VA authorization number requires retrieval from VA records, correction, and resubmission within the filing window. A valid number does not establish that every billed service was authorized. The episode of care, or SEOC, defines the permitted services, units, and visit lengths. Billing 60-minute sessions against a referral authorizing 30-minute visits is a scope mismatch, requiring comparison of the referral with the billed service.
Authorization expiration is a separate category from scope. Services provided after the authorization end date are denied regardless of medical necessity, so the authorization must be renewed before then. Timely filing is another distinct category, governed by the 180-day window from the date of service. When payer failures caused a delay, records of the disruption can help make the case for an exception. The final category is missing or incorrect primary insurance information, which requires accurate coverage details and the primary EOB.
The recoupment wave hitting VA Community Care providers by specialty
Payment does not end the exposure for CCN providers. When TriWest or PGBA identifies an overpayment, a recoupment letter can be followed by offsets against current and future claims. Leaving the network does not cancel the asserted debt. TriWest has said that practices with no future claims face collections. A practice concentrating only on submission denials can therefore miss a separate threat to current cash flow.
TriWest sent chiropractors pricing-adjustment recoupment letters tied to multiple procedure payment reduction, or MPPR, in 2025. MPPR is a Medicare payment policy adopted for the VA fee schedule. Its retroactive application to already-paid claims is the contested issue. Optum’s 2024 recoupments involving acupuncture cupping under CPT 97039 instead turned on authorization scope and were rescinded after providers demonstrated that the code was within their SEOC.
The acupuncture reversal and the Florida mental health case in 2026 establish that evidence-based disputes can succeed. They do not establish that every demand is invalid. VA is also recovering tens of millions of dollars directly from CHAMPVA providers following an error in its own claims adjudication system. Recoupment exposure therefore extends beyond the TPA layer, while the grounds for challenging each demand remain specific to the payment and its supporting records.
How to dispute a recoupment letter before the offset clock runs
For a practice receiving a letter, the first action is to check its deadline immediately. The clock runs from the letter date. The next action is to classify the stated reason before drafting a response. An MPPR or pricing dispute challenges the basis for retroactive application, while an authorization or SEOC dispute requires the original referral and comparison with billed services and units. Duplicate-payment allegations require EOB evidence showing what was received, and documentation, coding, or eligibility allegations require the relevant clinical and billing records.
The third action is a written dispute requesting the supporting rate calculation and, where applicable, the contractual basis for retroactive application. The legal basis is 38 U.S.C. § 1703D. It requires notice and an opportunity to dispute, with a determination before deduction unless waiting would jeopardize the Secretary’s ability to recover the full indebtedness. That exception limits the protection against an immediate offset.
If the amount would harm practice operations, the next action is a written compromise request under the same statute, submitted with the dispute. A written payment-plan request provides a fallback against a full offset at once. In parallel, a representative’s or senator’s caseworker can open a formal inquiry about the provider’s file. The Evans case supports that escalation route. The American Chiropractic Association’s April 2026 engagement with VA and TriWest leadership also produced reassessment of contracting fees and the right to contract without extra ancillary agreements, demonstrating a separate role for organized provider advocacy.
Working aged CCN and TRICARE claims before the timely filing window closes
The billing team should sort accounts receivable by denial category first and age second, so each group has a defined next action. Within those groups, approaching deadlines determine urgency. Erroneous OHI denials warrant immediate escalation as system errors. This prevents staff from pursuing primary-payer documentation for coverage that was incorrectly recorded.
The next step is to connect any requested filing exception to the actual disruption. The request should identify the specific disruption period, the date of service, and when the claim entered the payer’s system relative to that period. The 2025 provider-file failures and January 2026 rate validation hold provide distinct factual grounds. Neither automatically suspends the filing clock. Corrected claims still need all the documentation and should be resubmitted before the 180-day mark whenever possible.
Correction then follows the category already established. Staff obtain missing authorizations, reconcile billed units or service types with the referral, or attach the missing primary EOB. At the same time, prospective authorization tracking must continue so that new expiration denials do not accumulate behind the recovery effort. The recovery paths described here cannot fix an expired authorization after the service has been provided. Because successful appeals can still take significant time, oversight must cover the full AR aging curve, including claims beyond the latest 30-day bucket.
What systematic CCN billing operations look like compared with reactive ones
A reactive operation finds out about the problem when the money stops coming in. A systematic operation spots stalled claims before they risk missing the timely filing deadline. For CCN, that requires more than standard commercial billing benchmarks because authorization, COB sequencing, SEOC scope, and administrator-specific processing all affect collectability. Tracking AR aging in real time shows which claims have stalled. Payer-specific follow-up protocols then distinguish when a call is appropriate from when a written inquiry is needed.
Staff who have handled a TriWest disruption know how to document an exception request in ways that a provider manual alone cannot supply. Turnover can erase that knowledge unless the operation preserves it. Recoupment readiness exposes the gap particularly clearly. A reactive practice starts searching after a letter arrives, while a systematic practice has already found the MPPR-exposed claims, kept the original rate basis, and prepared dispute templates.
How AI-assisted billing changes the recovery math for CCN and TRICARE West claims
Automation is useful where the failure is repeatable and detectable. AI-powered claim scrubbing can flag missing authorization numbers, SEOC mismatches, and incorrect COB sequencing before submission. That reduces the volume entering the denial cycle. On the AR side, monitoring can flag claims approaching critical thresholds and initiate payer-specific follow-up. Staff working on claims with other payers have less need to watch for each aging claim themselves.
Authorization tools address an earlier point in the cycle. They can extract required clinical data from EHR records, populate payer-specific forms, and submit requests automatically, compressing approval time from days to hours. These tools reduce gaps in the authorization process that can later lead to authorization denials. They do not resolve contested recoupments or replace clinical judgment. People still need to review medical necessity and prior authorization challenges.
The appropriate model combines administrative pattern recognition with billing specialists who understand TriWest and Optum disputes. That distinction is particularly important for massage, chiropractic, and acupuncture practices under recoupment pressure. Software can support prevention, monitoring, and preparation of the claim record. A specialist must still connect the evidence to the disputed policy or authorization. The acupuncture and mental health reversals resulted from targeted human arguments.
What practices billing VA Community Care and TRICARE West should do before the next disruption
The preparation sequence starts before the visit. Practices should verify eligibility, the VA authorization number, SEOC coverage for the planned service and duration, and the authorization end date. Other active coverage must be identified and documented so that primary billing and EOB attachment occur in the correct order. AR protocols should then set points for escalation before claims near the halfway point of the timely filing window. Those protocols need explicit handoffs from automated follow-up to human review and, where appropriate, congressional inquiry.
Practices must keep complete records of their own. VA is replacing the five-region setup with two networks as current contracts expire in 2026, creating risk for documentation held only in an outgoing administrator’s system. Referrals, authorizations, EOBs, remittances, and rate confirmations should remain accessible to the practice. For MPPR-exposed timed therapy codes, particularly 97124, 97140, and similar codes, the original rate basis should be documented at the time of service. That evidence gives a future dispute a foundation before the letter arrives.
A recoupment demand should trigger review. The documented reversals justify disputing with evidence, although they do not guarantee a favorable result. More broadly, TriWest’s administrative failures extend to its prior contract period, and the OIG has identified oversight gaps in claims payment. Periodic disruption is therefore a sound operating assumption. Practices built around that assumption will be better positioned to recover before a processing failure becomes a missed deadline.