Pre-Submission Claim Scrubbing Against Live Payer Policy as a Denial Prevention Standard
Live-policy scrubbing catches coverage mismatches before payers deny claims.
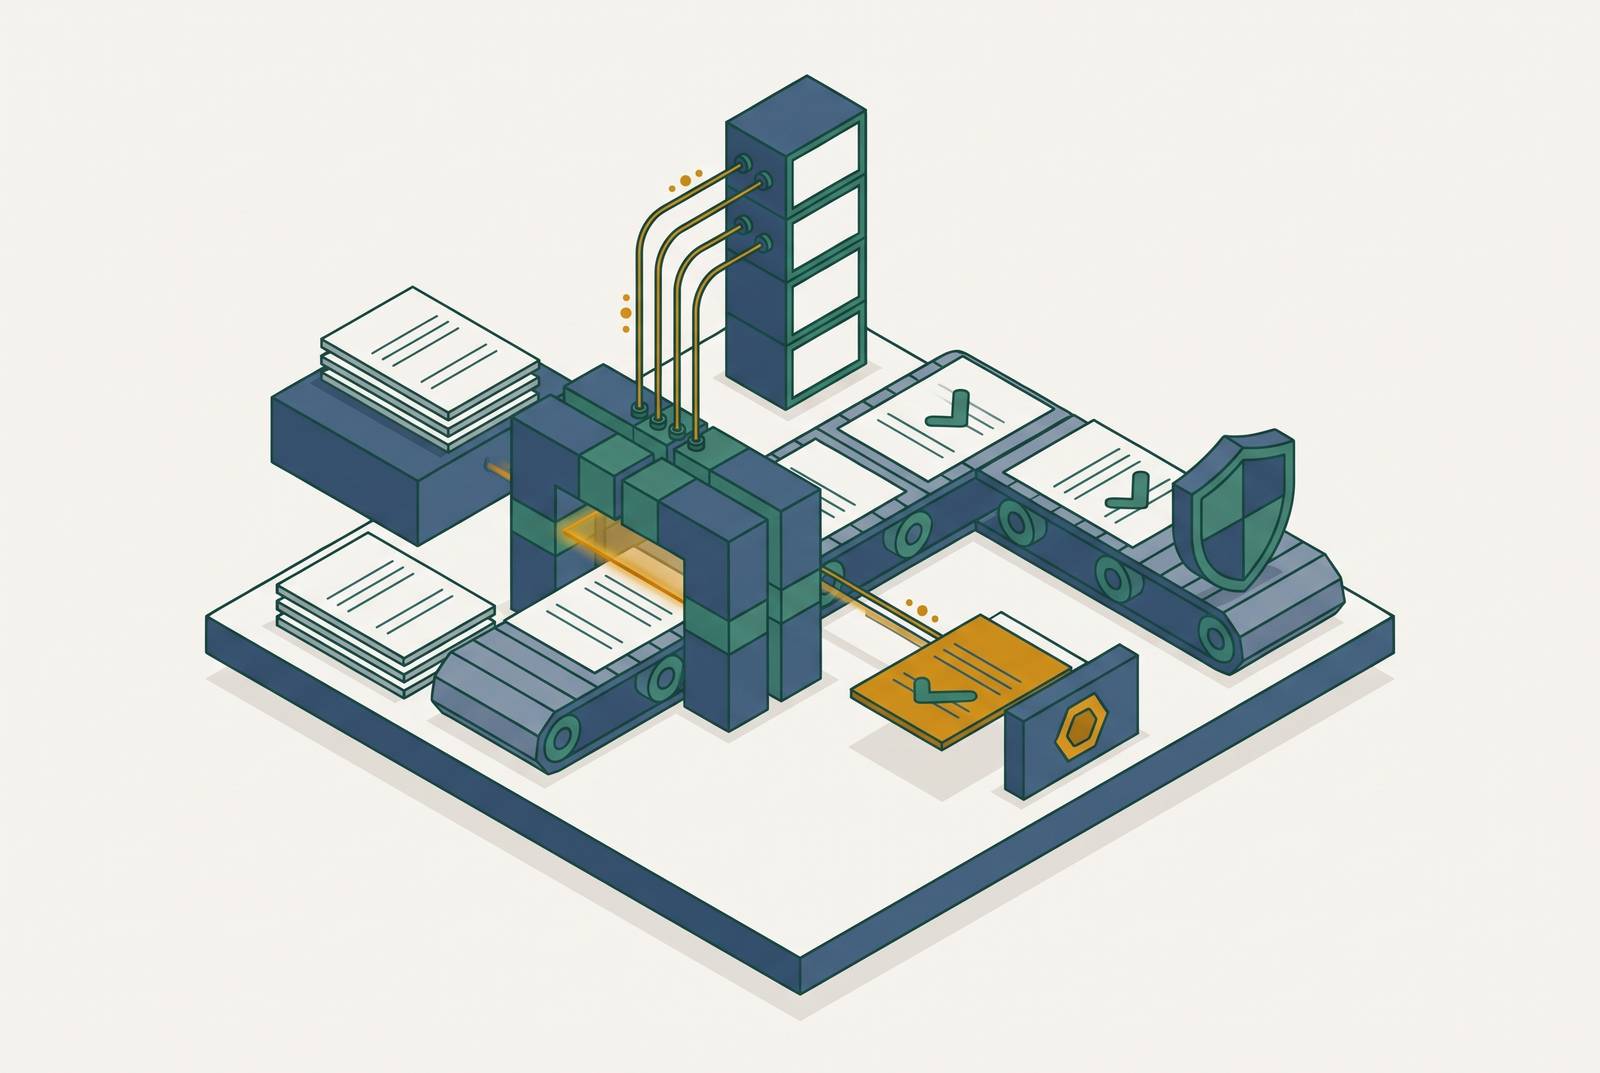
To prevent insurance claim denials, a small medical practice needs to check claims against current, plan-specific payer policy before submission, verify eligibility, and have specialists review clinical exceptions. Static edits cannot close the gap between a payer’s policy change and a practice’s discovery of it through a denial. Live-policy scrubbing should be a required part of pre-submission review.
Why payer-side policy changes are now the leading driver of claim denials
Denials are increasing as payer requirements change more frequently, making the problem broader than billing execution alone. Experian Health’s 2026 State of Claims survey of 204 healthcare professionals who make decisions on financial, billing or claims management matters found that three-quarters of providers say denials are rising. Nearly four in five say payer policies are changing more frequently, up sharply from the survey’s first year in 2022. The trend is not confined to data entry. Practices face a moving set of coverage and adjudication requirements even when their claim preparation remains consistent.
For the first time in the survey’s history, services not covered by the plan ranked as the top denial driver, overtaking missing or inaccurate data. Payer policies that change often ranked second, with nearly a third of respondents naming them as a cause. Coverage interpretation has become the central fault line. A claim can contain accurate information and still fail because the billed service does not meet the plan’s current requirements. Better claim construction remains necessary, but it cannot resolve a coverage-policy mismatch by itself.
The same survey found that nearly four in five respondents consider payer reimbursement more challenging, while nearly two-thirds say submitting a clean claim has become harder. Both measures have worsened each year the survey has run. That pattern changes the operational diagnosis for practices in 2026. A process designed chiefly to remove clerical errors does not address the leading reported causes of denial. Prevention must also address the speed at which payer requirements change.
How payer policy changes happen in practice, and how fast they move
Payer updates arrive on separate schedules, but their implementation dates can converge. The week of September 1, 2026 brought at least six separate policy updates across UnitedHealthcare, Aetna, Blue Cross Blue Shield of Michigan, BCBS Texas, and Molina Healthcare. UnitedHealthcare tightened lab test reimbursement across commercial, Medicare Advantage, exchange, and Medicaid plans. Its Medicaid rollout is staggered by state through November 2026, with some policies extending to December 2026, so the same test may be covered in one state and denied in another during the transition.
Aetna expanded its Claim and Code Review Program effective September 1, 2026, adding automated edits drawn from CMS, AMA CPT guidelines, and evidence-based clinical criteria. Those edits apply to commercial, Medicare, and student member plans, so claims that were accepted before now face new automated review. The payer also introduced a radiology payment reduction on that date tied to modifier CT for non-compliant imaging equipment.
Medical Mutual switched from MCG to InterQual for its medical necessity review criteria on April 13, 2026. MCG’s symptom-severity logic does not map cleanly onto InterQual’s objective clinical thresholds, episode-specific criteria, and defined progression pathways. Documentation must support the new criteria. Humana’s expanded prepayment review and clinical validation audits add another form of scrutiny, concentrating on high-cost, high-variance DRGs including sepsis, respiratory failure, and malnutrition.
Why a static scrubbing rule library cannot keep pace with continuous payer policy change
Generic claim scrubbing checks structural completeness, including formatting and missing fields. Payer-specific scrubbing goes further by applying the requirements of the plan being billed, because the same CPT code can face different rules across Medicare, Medicaid, and commercial plans. Yet specificity alone does not establish currency. An edit library can identify the right payer and still apply an outdated requirement. A scrubber using last quarter’s rules may therefore clear a claim that violates a policy changed last week.
The failure occurs between publication and implementation. Until the updated policy reaches the edit library, the practice has no pre-submission signal that its claim conflicts with the new requirement. The first signal may instead be a denial arriving weeks later. This infrastructure gap prevents even a careful biller following the available edits from relying on them to reveal a requirement they do not yet contain.
Clearinghouses provide another review layer and speed claim release, but their edits primarily test format and common payer requirements. They do not substitute for current, payer-specific checking of coverage and modifier requirements. Rejection and denial measure different outcomes. A practice can have few clearinghouse rejections while experiencing substantial payer denials because acceptance for transmission does not establish compliance for adjudication. Authorization-related failures expose the same limitation when eligibility, authorization requirements, diagnosis specificity, and modifiers are not checked against current policy before submission.
How does live-policy scrubbing prevent denials before submission?
Live-policy scrubbing checks a claim against the payer’s current published requirements, with rules updated continuously. When BCBS Michigan adds modifier SA on September 1, 2026, a live-rule system flags the missing modifier before the claim leaves the practice. The practice encounters the change as a specific correction requirement rather than discovering it through a later denial spike. Current policy becomes part of the submission decision.
That timing makes pre-submission review the point in the claim lifecycle where a practice can do the most to prevent denials. A mismatch corrected before release avoids the denial workflow that the mismatch would otherwise trigger. Staff do not have to wait for the payer’s response before learning which published requirement the claim fails. Checking against current policy closes the gap left by a static library, though it cannot predict every clinical interpretation a payer may use.
Eligibility verification must accompany this review because some failures originate in intake data. Most scrubber rule sets do not cover coverage mismatches and authorization problems, so these need a front-end check alongside scrubbing. Scrubbing cannot replace that check after the fact. The Experian survey found that providers working to reduce denials include those using digitized registration and automated payer-policy tracking.
The revenue and AR consequences of the scrubbing gap, measured at the practice level
The financial exposure begins with the payment delayed or put at risk by the initial denial. It then expands through the staff work required to diagnose the failure, locate the policy mismatch, correct the claim, and resubmit it. Each denial creates another administrative obligation. When denial volume exceeds what the practice can work immediately, unresolved claims accumulate while staff continue preparing new submissions.
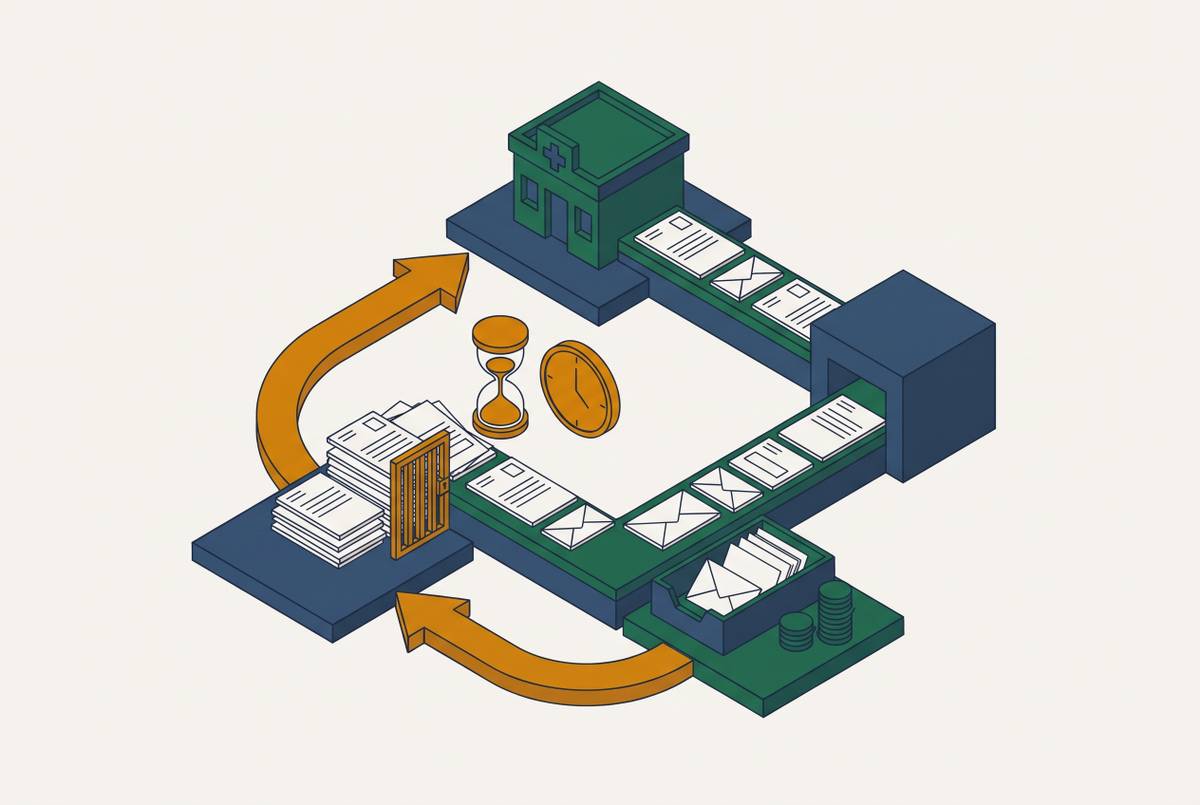
Accounts receivable aging compounds that burden because correction does not erase elapsed time. A claim that is rejected, corrected, and resubmitted has already consumed days in AR before the corrected version begins its adjudication cycle. A lower clean claim rate keeps adding to AR days each time a claim needs correction. By contrast, a claim that clears adjudication on first submission supports faster payment and lower administrative cost per dollar collected.
Appeals cannot reverse all of these consequences. Even when a practice recovers payment, it has already spent time correcting and defending the claim, and it can lose the revenue for good if denied claims are never resubmitted before recovery windows close. At the practice level, the relevant measures are therefore first-submission success, denial-related rework, AR aging, and claims left unrecovered. Looking only at eventual appeal success omits much of the cost created before recovery.
Authorization management failures are a significant source of collection difficulty in behavioral health, while cardiology shows a gap between best-in-class and average denial performance. The underlying failure determines the appropriate prevention step. Current-policy scrubbing addresses claim-level mismatches, while integrated authorization and eligibility checks address failures that originate before the claim is assembled. Neither approach can replace the other when both types of failure contribute to lost collections.
Why human expertise on payer behavior is required alongside automated rule-matching
Automated matching is strongest when a published requirement can be translated into an edit. Payers also apply clinical interpretations and prepayment reviews that a rule library cannot fully anticipate. A passed edit is not a clinical determination. Aetna’s internal medical necessity interpretations in respiratory, sepsis, and cardiac cases illustrate this boundary. Recognizing exposure to a proprietary clinical policy overlay requires knowledge of how the payer evaluates that category alongside knowledge of its published claim rules.
Humana’s prepayment clinical validation audits expose a related limitation because a claim may pass edit checks but remain held for payer-side human review. The practice response requires familiarity with the DRG categories that attract scrutiny and the documentation standards its auditors apply. The Medical Mutual criteria change also meant specialists had to understand how the two review frameworks differed and update guidance for practices before the change took effect. Recording a new policy date alone would not resolve the documentation gap.
This expertise becomes more useful as payer-specific knowledge accumulates. Experienced billers understand which documentation a payer scrutinizes, how it interprets clinical evidence, and which appeal arguments it accepts. Staff turnover can break that continuity abruptly. Automation alone cannot keep the judgment a biller has built over years of experience, so practices need billing specialists to back their live-policy tools. The machine-speed review handles repeatable mismatches, while specialists interpret exceptions and maintain the payer knowledge that makes the review effective.
What a practice should require from its pre-submission scrubbing operation to meet this standard
A practice evaluating its current process should begin with the rule-update mechanism and frequency. The relevant interval is the time between a payer’s policy change and its incorporation into pre-submission review. That interval should be days. Quarterly batch updates cannot keep up when requirements change all the time and sometimes without warning. The evaluation should also establish whether rules distinguish individual plans, since UnitedHealthcare’s lab restrictions differ across commercial, Medicare Advantage, exchange, and Medicaid lines.
Eligibility verification should be integrated with scrubbing. Coverage information and authorization requirements gathered at intake need to help guide the decision to submit a claim. Visibility should extend beyond individual claim corrections. A practice should be able to look at denial patterns by payer, claim type, and modifier so it can act on repeated problems before month-end and before recovery windows narrow. A low clearinghouse rejection rate is not evidence that these requirements are being met.
Where turnover, claim volume, or the number of payer contracts prevents reliable in-house monitoring and denial management, a billing operation combining live-policy automation with in-house specialists is an operationally sound alternative to manual management. A practice should compare the capabilities of an internal team and an outside billing partner by checking whether both have current plan-level edits, know how to handle clinical exceptions, and can respond to payer-specific denial patterns. Software alone satisfies only part of that standard.
EMR and clearinghouse integration should allow the improvement to occur in the scrubbing layer without forcing the practice to rebuild front-desk or clinical workflows. HIPAA compliance and data security are minimum requirements for any operation handling claim data, regardless of cost. Formatting checks remain necessary but are insufficient. The defining standard is whether the practice can identify a mismatch with current payer policy before submission and bring informed human judgment to the exceptions that automated matching cannot resolve.