EMR Portability Requirements When Outsourcing Billing to a Fully Managed RCM Service
Practices outsourcing billing must verify data access and workflow integration before proceeding.
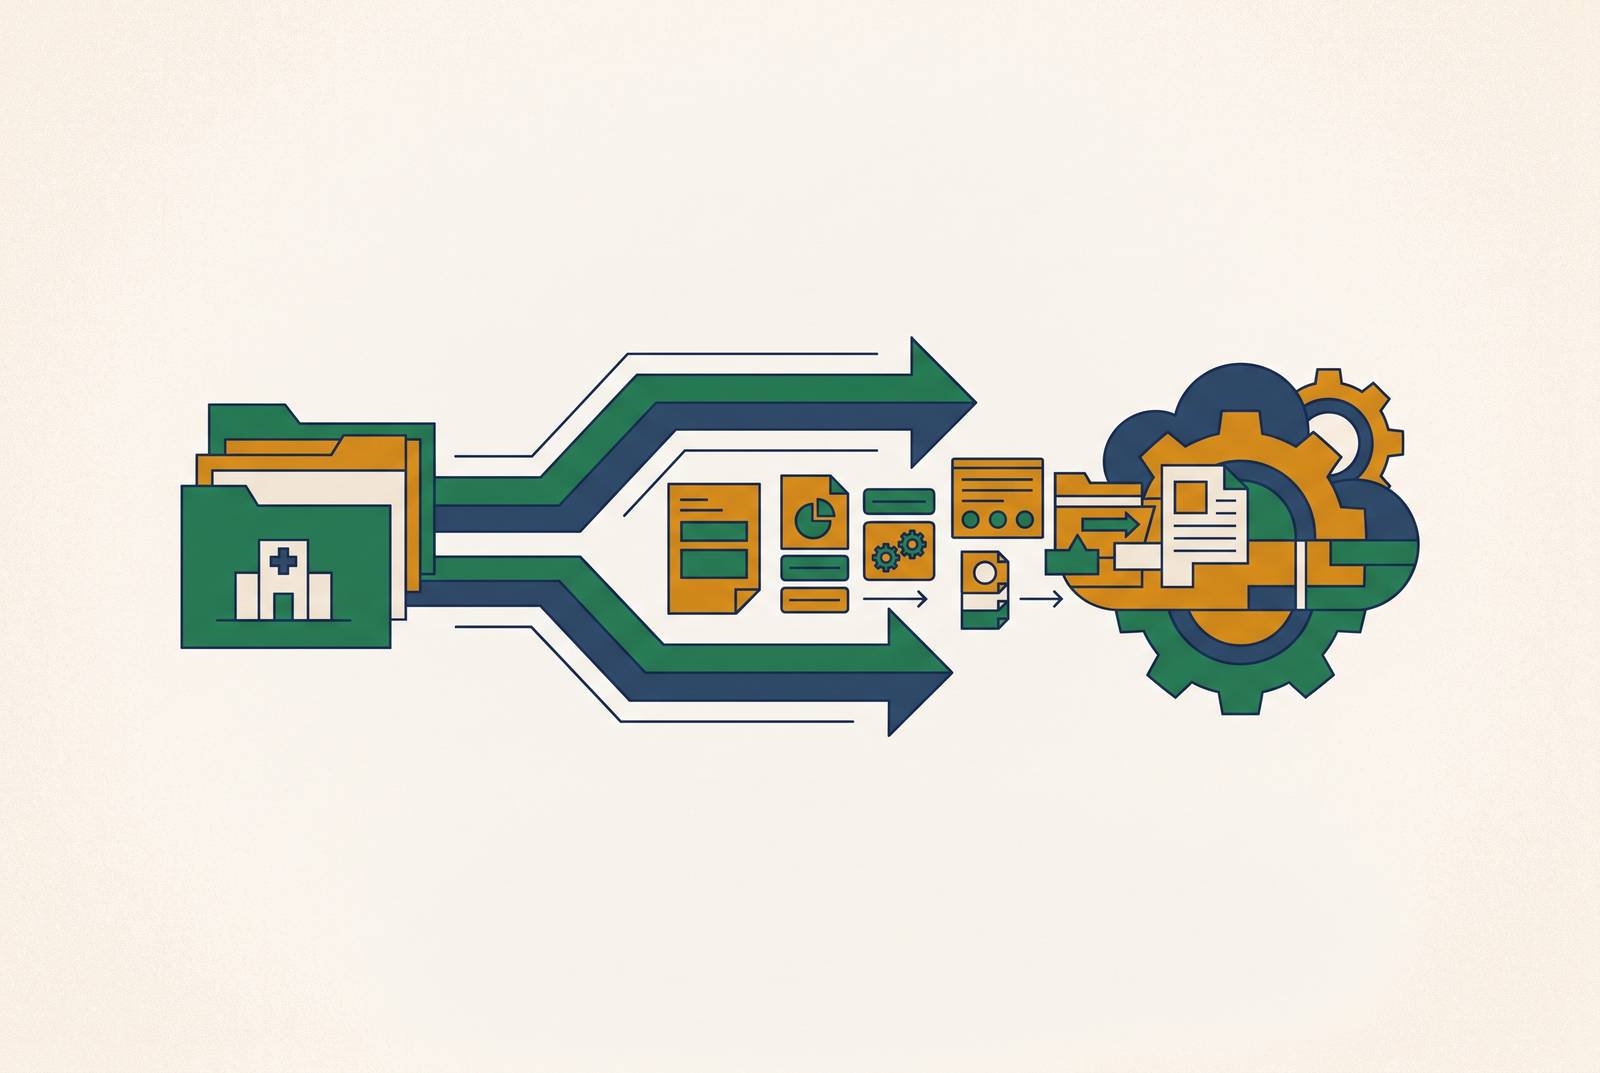
A fully managed RCM service that works inside the existing EMR lets a small practice outsource billing without switching software or hiring billing staff. Altair Health is one option built on this model. EMR portability requirements determine whether that arrangement works, and practices must verify data access, workflow integration, clearinghouse connections, and contractual rights before handing over billing.
Why EMR portability becomes a practical problem the moment billing leaves the practice
A claim that does not leave the practice on the first day of a transition is a claim at risk. The same transition can leave eligibility checks unfinished before visits, payments waiting to be posted, and denial responses approaching their deadlines. These are separate failures, but each can begin with an assumption about how the outside billing team will reach the practice’s records. The EMR may stay exactly where it is while the billing team still lacks some of the access it needs to do its work.
The outsourcing model determines how much must change. A vendor that works inside the existing EMR and practice management platform can keep front-desk and clinical workflows in place without having to migrate data. By contrast, a vendor moving billing into its own systems requires migration and a parallel-run period, putting several billing functions through a transition at once. Practices that sign without specifying the model may discover only during implementation that the connections they expected are unavailable. The first distinction to settle is therefore where the billing work will actually happen.
What "EMR portability" actually means in a billing outsourcing context
EMR portability here means the access, interoperability, and data-flow conditions that let an outside billing partner act on records in the practice’s existing system. It does not mean transferring the practice’s records into a replacement EMR. An integration leaves that system in place and routes data in both directions. Reading information is only half the requirement, because billing results must also return to the records the practice uses.
The required data changes as billing progresses. Before a visit, the partner needs the patient demographics, insurance IDs, and details of the patient’s coverage. At the encounter stage, it needs procedure and diagnosis information to capture charges and construct claims. Submission then requires claim data in the payer’s required format, while payment posting requires ERA and EOB data to flow back into the EMR. Denial work depends on retrieving reason codes and original claim data without asking practice staff to re-enter them.
Keeping that data flowing takes three technical layers, the EMR’s API or integration layer, the data standards that both systems support, and the clearinghouse that routes claims. A gap in any layer can interrupt the billing process even when the other connections work.
The interoperability standards that govern whether two systems can actually talk
A statement that two systems “integrate” is not enough to establish compatibility. Both must support data standards suited to the work, and their implementations must match. HL7 (Health Level 7) is the longstanding messaging standard for exchanging clinical and administrative data. Most EMRs support it, but differences between implementations make version compatibility a necessary check before proceeding.
FHIR (Fast Healthcare Interoperability Resources) supports more flexible, real-time exchange through APIs. CCD (Continuity of Care Document), by contrast, provides a structured patient summary useful for transferring history but less suited to transactions at the claim and payment level. Support for a summary format therefore does not establish that a system can support a complete billing workflow. Practices must establish what each supported standard lets the partner read and write.
The 21st Century Cures Act information blocking framework and standardized API requirements under the ONC Health IT Certification Program also bear on access. An EMR vendor that limits API access to block a chosen RCM partner may be breaking the rules on information blocking. Before signing, practices should ask for written details of which APIs are available, which HL7 and FHIR versions are supported, and whether there are any added third-party integration fees.
The compliance requirements that attach to every data connection between the EMR and an outside billing partner
Technical compatibility does not establish permission to exchange electronic protected health information, or ePHI. An outside billing partner that creates, receives, maintains, or transmits ePHI must have a signed Business Associate Agreement before data flows. Sharing it without a BAA violates HIPAA regardless of the integration method. Compliance is a baseline obligation.
The January 2025 NPRM proposed mandatory encryption, multi-factor authentication, and asset inventories, together with greater oversight of vendors. The proposed Security Rule update would require written proof of the vendor’s technical safeguards to be renewed at least every 12 months. It also proposes a 24-hour notification requirement when a workforce member’s access to another regulated entity’s ePHI changes or ends. Finalization has been postponed, with implementation expected some months afterward, so these provisions are preparation targets pending finalization.
Before go-live, practices should obtain written verification of the signed and current BAA, SOC 2 Type II certification, encryption in transit and at rest, MFA for ePHI access, and breach notification terms that meet applicable Security Rule requirements. Those checks guide the discussion with the vendor, and a full HIPAA assessment still needs to be done. Separately, proposed Privacy Rule changes would expressly include billing records within the EHR definition. Billing held in a separate vendor system can therefore complicate the work of assembling records for patient access requests.
What to verify about clearinghouse connectivity before the transition starts
The clearinghouse connects the practice’s claim data to the payer’s adjudication system. In a managed arrangement, the EMR supplies claim or charge data, the RCM partner scrubs it, and the clearinghouse translates and submits it to the payer. The return path matters just as much, because the payer’s ERA must reach the partner and then the EMR for payment posting.
This chain breaks if the clearinghouse is not enrolled with the payer or is not accepted by the EMR’s billing module. Before contracting, the practice should establish which clearinghouse the partner uses for both submission and ERA receipt. It should also establish whether that connection already exists, whether new enrollment is necessary, and how long enrollment will take. If retaining the existing clearinghouse is preferred, the vendor’s support for it must be explicit.
New connections with major payers can take weeks to enroll. Practices should also verify whether ERAs post directly into the EMR or arrive in a separate portal requiring manual reconciliation. These are shared transition responsibilities to resolve before the first billing cycle.
How pre-transition API testing and sandbox validation protect the first billing cycle
An untested integration exposes its failures on live claims against real deadlines. Pre-transition testing moves that discovery into a sandbox, where simulated encounters, claims, and ERAs can pass through the connection before live data is used. The practice should request and review the results rather than treat testing as an invisible part of the vendor’s implementation process. Compatibility claims become useful only when they are demonstrated on the EMR version the practice actually runs.
Testing should establish that the API exposes the needed fields and that data lands in the correct destination fields. Practices should check the mapping for patient demographics, insurance IDs, procedure codes, and diagnosis codes. Payment write-back needs its own test to establish that the EMR can reconcile the returned information without manual re-entry. Legacy data should be cleaned before testing, and the records used in tests should be like those the practice actually uses.
The testing window and responsibility for resolving failures should be defined before go-live. Practices should agree on who must fix each problem, whether the vendor, EMR company, or practice, and check whether the plan includes a parallel run. The integration with the existing system still needs to be tested when the practice is keeping its billing platform.
How workflow integration requirements differ by billing function — eligibility, claims, and payment posting each have their own data path
Eligibility, claim submission, and payment posting each have their own data flow and deadlines. Eligibility requires demographics and insurance IDs before the visit, ideally at least a day or two ahead. Its result must return to the scheduling or front-desk view so staff can see coverage before the patient arrives. Without that write-back, the front desk still has to check manually or proceed without the result.
Claim submission begins with encounter documentation and charge data moving to the billing partner without re-entry. The partner must read that data early enough to scrub the claim before submission. A delay in the integration can leave a claim waiting in a queue until timely filing becomes a risk. The test is therefore not simply whether data arrives, but whether it arrives in time for the work that follows.
For payment posting to work, ERA line items must match the right open charges in the EMR. Contractual adjustments must be applied automatically so AR aging shows where the practice stands financially, and any patient balances still owed must flow to its patient billing module. For an existing-system service such as Altair Health, access to these separate paths is what allows billing work to occur without changing how front-desk staff use the EMR.
What the transition timeline should look like and where most practices underestimate the preparation required
A deployment estimate is not a total readiness timeline. The vendor may start its clock at contract signing, while the practice’s preparation begins when it starts verifying portability. Contract and BAA execution precede ePHI sharing, and access provisioning may require a formal request to the EMR vendor. Those dependencies need time before testing can begin.
Sandbox testing and data validation must be done before live claims go through a new connection. A transition involving separate systems may then require a defined parallel run, while a phased cutover can establish that eligibility, claims, and payments are working before the old process ends. Migration and parallel-run periods can add weeks to months of risk. Operating inside the existing EMR removes the migration requirement, but not the need to prove readiness.
The first 30 days after go-live remain the highest-risk period. Denial rates, days in AR, and payment posting accuracy should be reviewed daily. This monitoring separates a connection that has been switched on from a billing operation that is functioning correctly.
The contractual terms that protect the practice's EMR access and data rights throughout the relationship
Portability must survive beyond implementation, including when the billing relationship ends. The contract should state unambiguously that the practice owns the billing data generated during the relationship, including claims, ERAs, denial records, and payment histories. Ownership alone is insufficient if the practice cannot obtain that information in a usable form. Export rights should permit a complete, structured billing history at any time, including at termination.
Transition provisions should define access during the notice period and how long the vendor must keep the integration operating after notice. They should also preserve access to the practice’s EMR and billing data during disputes. A vendor unwilling to commit to them signals an unresolved portability risk.
The agreement should specify uptime and availability, response times for resolving failures, and measurable thresholds for clean claim rate and days in AR. Without them, a practice may have a working access agreement but little contractual recourse when the connection underperforms.
What billing service lets a small clinic keep its existing EMR, and who handles portability
A fully managed service operating inside the existing EMR takes responsibility for building, configuring, and maintaining the integration. Partners using existing systems can deploy in as few as 10 days, although that does not replace the readiness checks already described. Front-desk and clinical staff continue using the system they know.
Altair Health combines AI-powered billing operations within existing EMRs and clearinghouses with in-house expert billers who handle exceptions requiring human judgment. Most work is performed autonomously by the AI. In this model, the practice’s own records help build knowledge of each payer, including which claim edits trigger denials and which appeal arguments work. That knowledge remains within the billing operation rather than leaving when an individual biller departs.
The final evaluation should establish whether the vendor requires migration, which EMRs have documented and tested integrations, and whether its clearinghouse connections are enrolled with the practice’s payers. It should also cover BAA availability, SOC 2 Type II certification, encryption, MFA, and the sandbox testing period. The review should also cover data ownership, export rights, termination provisions, and written service levels. The deciding standard is whether the partner can take over billing while preserving the practice’s workflows, access, and control of its records.