The Break-Even Calculus Private Practices Use to Decide Between Internal Billing and Full Outsourcing
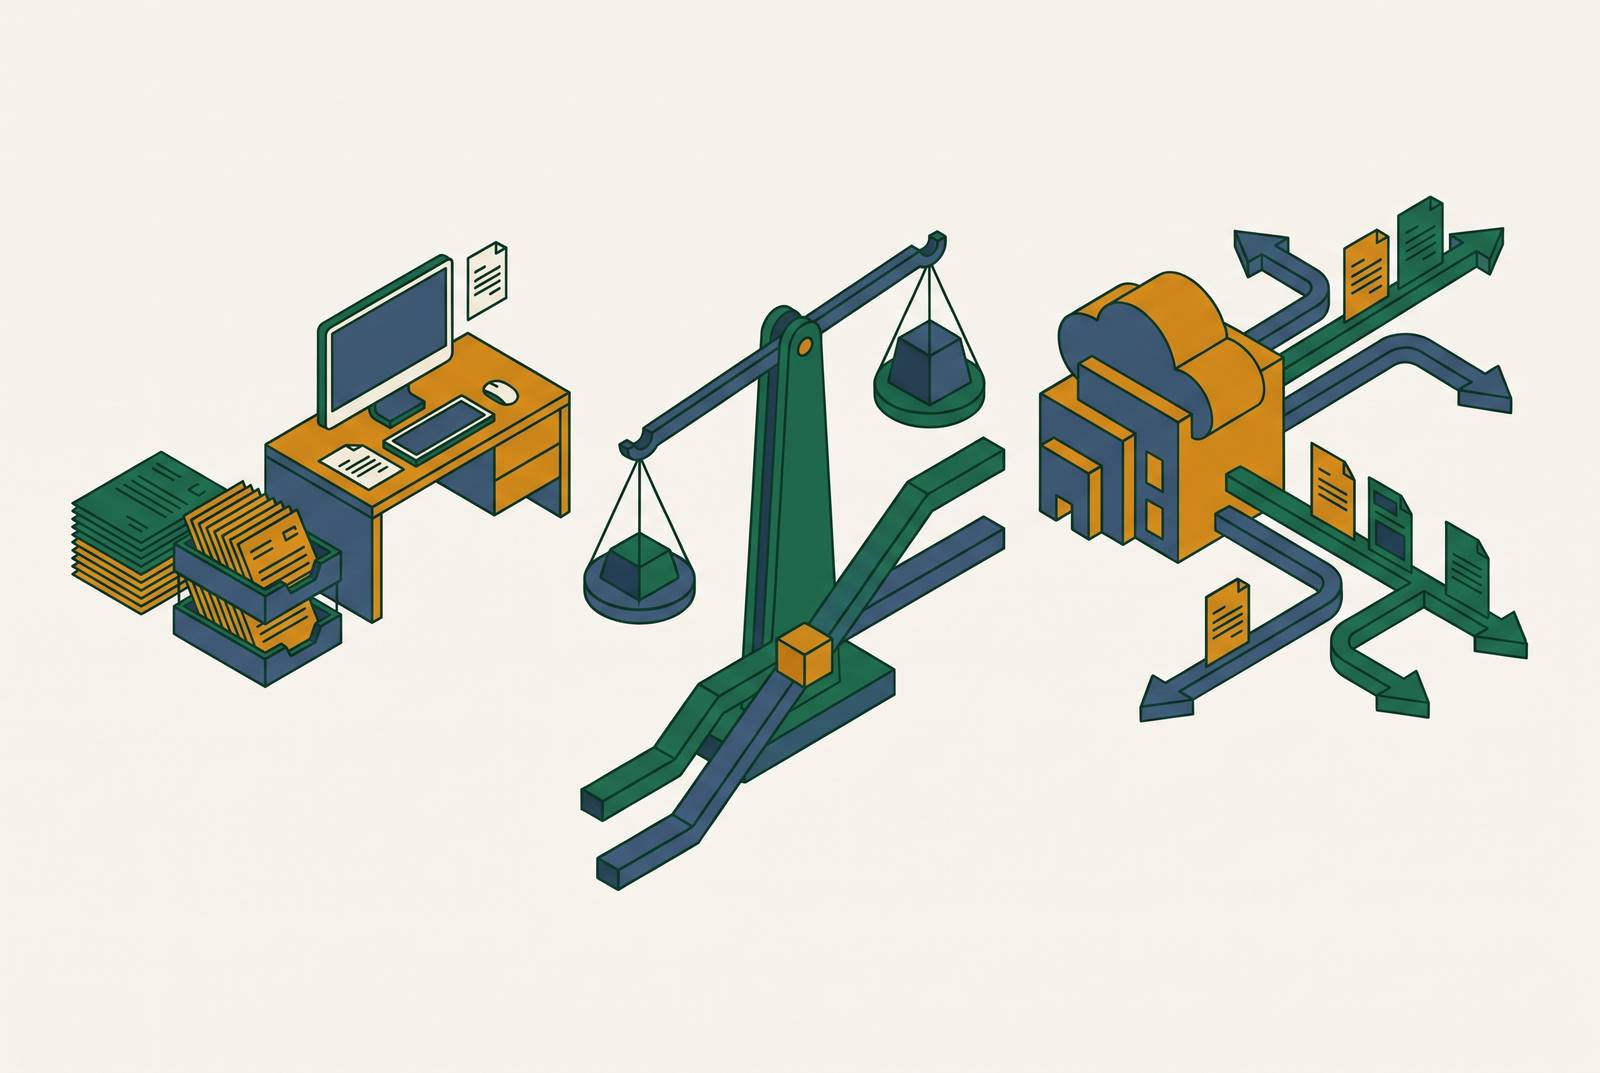
Outsourcing medical billing is worth the cost when it leaves a practice with more net revenue than a fully loaded in-house operation, after fees, transition costs, and retained staff work. Small practices are at a disadvantage when they have too few claims to support dedicated billing staff. The break-even calculation therefore compares total costs and recoverable revenue.
Why salary-only comparisons produce the wrong answer
Comparing a biller’s annual salary with an outsourcing percentage weighs just part of the in-house cost against the price of a broader service. Salary excludes the infrastructure, supervision, and coverage needed to turn submitted claims into collected revenue. The vendor fee excludes some costs as well. But the in-house undercount is structurally larger because payroll presents a billing operation with several expenses as a single position.
That mismatch favors the wrong measure of value. A lower visible expense can coexist with higher collection costs or more revenue left in unworked denials. An outsourcing percentage that looks low can also hide services that are billed separately.
What fully loading in-house billing cost actually requires
Base salary is the first verifiable line item. Employer payroll taxes and benefits belong next to it, drawn from payroll records. Practice management and billing software need another line for the actual charges for seats and subscriptions. Clearinghouse fees belong separately because per-claim transaction costs rise with volume. Each expense needs its own entry.
Training costs cover education each year, certification renewals, and the time it takes to learn payer-policy changes. Audit and compliance overhead covers work done by the practice or paid for outside it. Management time also has a cost. The administrator hours spent supervising billing, resolving problems, and reviewing performance draw capacity from other practice operations, even when no separate billing-management position appears on payroll.
Turnover and vacancy require a further allowance for recruiting, lost productivity, and accounts receivable aging while the position remains unfilled. These costs are less regular than software invoices, but irregularity does not make them absent. Unworked denials require a different treatment. They are lost collections, so they belong in the later revenue comparison and must be kept out of payroll expenses to avoid counting them twice.
Turnover as a recurring reset of billing institutional knowledge
A resignation removes more than billing labor. It can erase the practice’s working memory of which modifiers a payer rejects, what documentation triggers an insurer’s audit, and which appeal language has succeeded. In a small team, that knowledge may reside in one or two people. Accounts receivable can grow within weeks, before a new hire gets up to speed. Hiring someone fills the seat, but learning how to handle each payer takes more time.
Stability is not the same as structural resilience. When collections depend on one person’s accumulated knowledge, the practice remains vulnerable to that person’s departure, regardless of how unlikely it seems today. Losses during the vacancy and learning period may exceed the recruiting invoice.
An organized billing operation can keep what it knows about payer behavior patterns when staff change and use lessons from one client to help others. Knowledge compounded in-house may belong to the employee. Knowledge compounded within a billing organization becomes an organizational asset serving the practice’s revenue cycle.
What the outsourcing fee actually covers — and what it does not
A quote of “six percent of collections” does not establish the total outsourcing cost. Setup and onboarding may come with separate charges to connect to the practice’s existing EHR or practice management software. Internal coordination remains necessary as well. The practice still supplies accurate patient information, handles its share of patient billing inquiries, and manages the vendor relationship.
A well-structured fee typically covers claim scrubbing and submission, payer follow-up, denial management and appeals, and AR aging analysis. It may also include patient statements, payment posting, clearinghouse and EDI processing, and periodic performance reporting. Coverage must be established in the contract. Some companies charge separately for patient statements, credentialing coordination, appeals, or eligibility verification, so identical percentages can purchase different scopes.
Exit conditions belong in the same review. Long commitments, early-termination penalties, and restrictions on data handoff can create costs that a percentage quote does not reveal. The practical safeguard is to obtain the service terms, termination clause, and data-handoff protocol in writing before signing.
How to calculate the break-even rate specific to a practice
The starting calculation divides fully loaded annual in-house billing cost by annual net collections and expresses the result as a percentage. That percentage is the practice’s cost-parity benchmark. A quote below it is cheaper on cost alone only if outsourcing’s additional expenses do not consume the difference.
For a six percent quote, the annual service fee is six percent of the practice’s annual net collections. Setup charges, excluded services, and retained coordination costs must then be added for the period being compared. If that total equals fully loaded in-house cost, the models have reached cost parity. If it is lower, outsourcing has a cost advantage before any revenue improvement is considered.
This distinction separates the benchmark from the affordable headline rate. Dividing outsourcing overhead by the same collections figure shows how much room those expenses consume beneath the benchmark. Flat-fee and per-claim proposals can be converted to comparable annual costs using actual claim volume. Flat fees provide predictability, but their economics may be less favorable when volume fluctuates. Actual payroll, collections, and contract terms make this calculation usable.
How practice size and claim volume shift where the break-even lands
In-house economics improve when claim volume fully uses dedicated staff and spreads fixed infrastructure costs across more claims. Below that level, the practice pays for capacity it cannot fully use. Small practices face this constraint most directly. A percentage-based outsourcing fee ties the service expense to collections rather than requiring the practice to support an entire internal billing function.
Higher volume can reverse that advantage when a practice has stable, certified staff and modern practice management software. Even then, submission capacity is not the only requirement. Someone must be funded to work denials and aged AR. A busy billing team can process current claims while leaving the most difficult collection work unresolved.
There is no defensible universal provider-count cutoff. Staff cost, specialty, denial rate, software maturity, and the vendor quote all move the crossover. The strongest in-house case combines sufficient volume with the staffing depth and collection performance needed to use that scale effectively.
Specialty billing complexity as a multiplier on in-house cost
Even with similar claim volumes, the amount of work can vary widely because of denials, prior authorizations, and the documentation each specialty needs. In neurology, local coverage policies lead to denials, and Medicare Advantage prior authorization brings delays. Pain management adds high denial exposure and controlled substance documentation requirements. These are distinct workloads.
Behavioral health also has more authorizations to handle and stricter rules for clinical documentation than primary care. The resulting burden falls on staff who must track payer-specific requirements while continuing submission and follow-up work. Policy monitoring becomes part of collection capacity. A small team’s inability to follow changes across many payers can appear later as accumulating denials and falling collections.
This complexity affects both sides of the comparison. Outsourced fees can be higher for demanding specialties, while internal costs rise through training, documentation work, appeals, and supervision. An AI-assisted billing operation that aggregates payer behavior across clients can surface changes and apply a correction across affected practices. Its economic value depends on whether that capability closes a real gap in the practice’s current operation.
How the payer environment in 2026 changes what denial management costs in-house
Automated payer screening changes the workload behind a billing budget. Machine-learning models can flag utilization patterns, downcode evaluation and management levels, and generate denials faster than a small team can review them individually. Lower-value denials still require staff attention. As a result, unchanged salaries can conceal a growing backlog or a larger need for appeal capacity.
CMS’s 2024 Medicare Advantage prior authorization data shows that only a small fraction of denied requests were appealed, while the great majority of appealed decisions were overturned. That result identifies a substantial opportunity within appealed requests. It does not establish that every unappealed denial would have been reversed. For the cost calculation, the relevant issue is whether the practice has enough capacity to identify and pursue recoverable requests.
CMS’s prior authorization rule requires impacted payers to provide specific denial reasons beginning in 2026. Those reasons can support appeals, but staff must track and act on them at the request level. CMS sets most API compliance dates for January 1, 2027, while the operational requirements start in January 2026. Manual prior authorization workload therefore persists through at least 2026.
CMS’s WISeR Model began its initial performance year on January 1, 2026, in Arizona, New Jersey, Ohio, Oklahoma, Texas, and Washington. It adds Original Medicare prior authorization work for what the model covers. The practice must account for the workload its current payer environment creates.
Where recovered revenue enters the break-even calculation
Cost parity is only the first comparison. The next is how much revenue each model leaves after collection expenses, including any improvement in denial recovery and net collection rate. A practice with substantial unworked denials has more potential upside than one already collecting effectively. Recovery depends on the starting gap. It cannot be assumed from the decision to outsource alone.
Unworked denials create the most direct loss because revenue that is never successfully resubmitted can be forfeited. Shorter AR days help in a different way, by getting cash to the practice sooner. Faster payment is not automatically additional revenue.
AI-assisted claim scrubbing and denial pattern recognition, combined with billing specialists who work exceptions, can support earlier action on denials. The relevant test is whether the proposed operation can improve the practice’s measured performance enough to justify its total fee. A hybrid arrangement is also legitimate. The practice can keep front-end work such as scheduling and eligibility verification and outsource claims, denials, and AR, with its own costs and split of who does what.
How do you know whether your practice should outsource billing or keep it internal?
The practical decision starts with the practice’s own records. An administrator should assemble payroll, benefits, taxes, software, clearinghouse charges, training, compliance costs, management time, and turnover or vacancy losses. Dividing the annual total by annual net collections establishes the internal benchmark. Vendor proposals can then be tested against it after adding setup fees, exclusions, and retained coordination work. Exit terms belong in that review, before the financial decision.
Performance needs a parallel assessment. Initial denial rate, days in AR, aged AR, and net collection rate show where better execution could recover revenue or accelerate cash. Available benchmarks can help size the gap without turning it into a guaranteed return. The decisive questions are whether denials are being worked, who owns aged AR, and whether the proposed service includes the work needed to improve both.
Risk then qualifies the arithmetic. High-denial specialties, unstable staffing, limited management bandwidth, and dependence on a single biller strengthen the case for outsourcing. High, stable claim volume, a tenured certified team, modern software, and top-decile performance strengthen the case for keeping billing internal. Neither profile replaces the calculation.
A billing audit is the concrete first step. A well-structured billing partner can help reconcile costs, examine denial and AR performance, and define the work covered by a proposal, turning an abstract percentage comparison into a decision grounded in the practice’s own numbers.